2019年4月17日水曜日

PIONEER 3:経口セマグルチド vs DPP4阻害剤

PIONEER 10
http://www.novonordisk.co.jp/content/Japan/AFFILIATE/www-novonordisk-co-jp/Extweb/news/2018/10/04/18-27.pdf

ってのもあったが、PIONEER 1、PIONEER 2、PIONEER 6までは確認したが・・・

今回 PIONEER 3


Effect of Additional Oral Semaglutide vs Sitagliptin on Glycated Hemoglobin in Adults With Type 2 Diabetes Uncontrolled With Metformin Alone or With Sulfonylurea
The PIONEER 3 Randomized Clinical Trial
Julio Rosenstock, et al. ; for the PIONEER 3 Investigators
JAMA. 2019;321(15):1466-1480. doi:10.1001/jama.2019.2942

経口GLP-1アナログであるセマグルチド(3, 7, 14 mg/日)投与 vs シタグリプチン (ジャヌビア、グラクティブ)100mg/日投与比較
2型糖尿病患者 “メトホルミン±SU剤”治療中コントロール不良
26週後、HbA1c改善は、セマグルチドの方がシタグリプチン


ランダム化 1864名(平均年齢 58 [SD, 10]歳、平均ベースラインHbA1c 8.3% [SD, 0.9%]; 平均BMI 32.5 [SD 6.4]、女性 47.2%)
トライアル完遂 1758(94.3%)、早期中断 セマグルチド 3mg/日 16.7%、7 mg/日 19.1%、14 mg/日 19.1%、シタグリプチン 13.1%

ベースラインからweek 26までの効果差

  • セマグルチド 7mg/日、14mg/日 はシタグリプチンに比較して HbA1c有意低下 (差 , –0.3% [95% CI, –0.4% to –0.1%] 、–0.5% [95% CI, –0.6% to –0.4%]) p< 0.001
  • 体重差 (差 , –1.6 kg [95% CI, –2.0 to –1.1 kg] 、 –2.5 kg [95% CI, –3.0 to –2.0 kg]) p< 0.001

セマグルチド 3mg/日は HbA1cに対し非劣性示せず

両エンドポイントのWeek 78評価は対シタグリプチン比較し、セマグルチド 14 mg/日は統計学的有意差大きい


2019年4月16日火曜日

SGLT2i:心筋虚血時ブドウ糖代謝→ケトン体/FFA/BCAA代謝利用へ代謝シフト

SGLT-2阻害剤、エンパグリフロジン(ジャディアンス)はブタモデルにおいて心筋代謝をブドウ糖から他のエネルギー効率の良い代謝、ケトン体・遊離脂肪酸・BCAAへシフトさせ、血糖降下作用外で心筋保護作用を示す。


Empagliflozin Ameliorates Adverse Left Ventricular Remodeling in Nondiabetic Heart Failure by Enhancing Myocardial Energetics
Carlos G. Santos-Gallego, et al.
Journal of the American College of Cardiology Volume 73, Issue 15, April 2019
DOI: 10.1016/j.jacc.2019.01.056
http://www.onlinejacc.org/content/73/15/1931

背景 2型糖尿病対象のEMPA-REG OUTCOME (Empagliflozin Cardiovascular Outcome Event Trial上のエンパグリフロジンの心へのベネフィットは血糖降下作用だけでは説明できない

目的 仮説:エンパグリフロジン心へのベネフィットは、心筋fuel metablosimとして糖からケトン体へswitchingして、心筋エネルギー産生改善効果をもたらすのではないか?

方法 心不全を非糖尿病豚(n=14)で左前下行枝近位2時間バルーン閉塞にて誘発。動物をランダム化2ヶ月(エンパグリフロジン vs プラシーボ)。心MRIと3-Dエコーにて評価。
心筋metabolite consumptionを冠動脈及び冠状静脈洞から疑似採血採取にて解析。
心筋サンプルで分子学的評価。非心筋梗塞豚と比較。


結果 両群とも同じ初期心筋障害であったが、エンパグリフロジン群では対照群に比較し、2ヶ月後障害的remodeling緩和(左室筋量、左室拡張減少、左室sphericity減少)
左室収縮機能(左室駆出率、心臓超音波-評価strain)改善、neurohormonal activationも改善。
非心筋梗塞と比較した対照群では心筋ブドウ糖消費増加し、主にそれは嫌気的解糖によるもので、一方遊離脂肪酸及びBCAA利用減少
エンパグリフロジン治療豚はブドウ糖消費せず(心筋ブドウ糖摂取及びブドウ糖関連酵素の減少)、代わりに、ケトン体、遊離脂肪酸、BCAA利用へswitchがなされた(3つの代謝対の心筋摂取増加、これら酵素の発現・活性亢進し、これがケトン体/遊離脂肪酸/BCAA代謝増加を示唆)
エンパグリフロジンは心筋ATP contet増加し、心筋仕事効率促進した

結論 非糖尿病ブタモデルでエンパグリフロジンは不利な心筋リモデリングや心不全を緩和を示し、心筋fuel utilizationをブドウ糖利用からケトン体、遊離脂肪酸、BCAA利用へswitchし、心筋のenergeticsを改善し、不利な左室リモデリングを緩和する


”健常心筋のエネルギー源は主に脂肪酸のβ酸化に依存していますが、虚血や低酸素状態になるとブドウ糖を利用した解糖系へ移行 ”する。
この研究で代謝機構の変化、すなわち "fuel hypothesis":SGLT2iの心筋保護作用メカニズムが示唆。心不全での"glucocentric metabolism"という不適合(maladaptive)があり、それを改善するメカニズムの説明の一つとなるらしい


2019年4月15日月曜日

GINA2019:Step 1変だぞ

時々、なんじゃこれは・・・と思うガイドライン変更がある 大概は、末端のちっぽけな開業医はこれに抗うことができず、素直に従うことが多いわけだが・・・


要するに、初っぱなから、シムビコート 頓服吸入をしても良いよ・・・でも、「off label」、認可してないから責任取らないよぉ・・・って、ひどすぎない?


自己矛盾に満ちた内容のGINAガイドライン

https://ginasthma.org/reports/


言い訳から入る「2019年改訂のバックグラウンド」

「軽症喘息患者こそた重症有害事象リスクである」
  • 急性喘息成人の30−37%、准致死性喘息の16%、成人喘息死の15-20%が3ヶ月以内に“週毎症状”無し
速効性の短時間作用β2刺激剤(SABA)が喘息の第1選択薬剤であった

SABAのリスク強調

  • β受容体downregulation、bronchoprotection低下、気道過敏性リバウンド、気管支拡張反応低下
  • アレルギー反応増加、好酸球気道炎症増加

SABA過度使用によるリスク

  • 年3canister以上使用はED受診リスク増加
  • 年12canister以上使用は死亡リスク増加


SYGMA trial programme
The SYmbicort Given ‘as needed’ in Mild Asthma (SYGMA) trial programme is composed of two, 52-week Phase III, randomised, double-blind, multicentre, parallel-group trials in more than 8,000 patients aged 12 years and older with a clinical diagnosis of asthma for at least six months, who would qualify for treatment with regular low-dose ICS maintenance.5
  • SYGMA 1 randomised 3,849 patients to evaluate the efficacy and safety of Symbicort Turbuhaler (200/6 µg*) ‘as needed’, compared with terbutaline (0.5 mg†) ‘as needed’ and budesonide (200 µg) twice-daily plus terbutaline (0.5 mg†) ‘as needed’.2The primary objective was to demonstrate that Symbicort given ‘as needed’ is superior to terbutaline ‘as needed’, as measured by electronically-recorded well-controlled asthma weeks.2
  • SYGMA 2 randomised 4,215 patients to evaluate the efficacy and safety of Symbicort Turbuhaler (200/6 µg*) ‘as needed’, compared with budesonide (200 µg) twice-daily maintenance plus terbutaline (0.5 mg†) ‘as needed’.1 The primary objective was to demonstrate that Symbicort given ‘as needed’ is non-inferior to budesonide plus terbutaline ‘as needed’, as measured by the relative rate of annual severe asthma exacerbations‡.1
https://www.astrazeneca.com/media-centre/press-releases/2018/new-england-journal-of-medicine-publishes-two-trials-for-symbicort-as-an-anti-inflammatory-reliever-therapy-as-needed-in-mild-asthma16052018.html


 このSYGMA研究登録者たちはそもそも" mild asthma and were eligible for treatment with regular inhaled glucocorticoids."とあるように、喘息治療が既になされている症例であって、治療naive患者たちの選択ではない。


"SYGMA 1"


喘息症状コントロールに関して、"as needed budesonide-formeterol"は、"as-needed terbutaline"に比べ優越、"budesonide-formeterol" maintenance therapyに対しては劣性。 急性増悪率に関しては、両"budesonide-formeterol”群は"as-needed terbutaline"より急性増悪率低い。 "budesonide-formeterol used as needed"は維持療法に比べステロイド必要量少ない (Funded by AstraZeneca; SYGMA 1 ClinicalTrials.gov number, NCT02149199.)


<結論としては>
シムビコート維持療法が喘息コントロールとしては最も優れている
急性増悪を治験ターゲットにした場合、吸入ステロイド処方なしのテルブタリン頓用の急性増悪多かった。


後者はステロイド吸入してないのだから当たり前と思う。

そもそもがこのSYGMA-1は、"The primary objective was to investigate the superiority of as-needed budesonide–formoterol to as-needed terbutaline with regard to electronically recorded weeks with well-controlled asthma"ということで、喘息コントロールをプライマリアウトカムとした報告で、これをもってガイドラインの根拠とするのはおかしいわけで、証拠に言い訳がましい記載が混入している。


2019年4月11日木曜日

2型糖尿病へのSGLT2iの体組成、体液、RAASへの影響

BMC Cardiovascular Diabetology

Effect of SGLT2 inhibitors on body composition, fluid status and renin–angiotensin–aldosterone system in type 2 diabetes: a prospective study using bioimpedance spectroscopy
Anja Schork, et al.
Cardiovascular Diabetology201918:46
https://doi.org/10.1186/s12933-019-0852-y
https://cardiab.biomedcentral.com/articles/10.1186/s12933-019-0852-y

6ヶ月時点で、HbA1c 0.8% (IQR 2.3 ; 0.4)、体重 2.6 kg (1.5; 9.3) 、BMI 0.9 kg/m2 (0.4; 3.3)減少

Bioimpedance spectroscopyにて脂肪組織mass、脂肪組織index有意減少するも、除脂肪組織parameterは安定


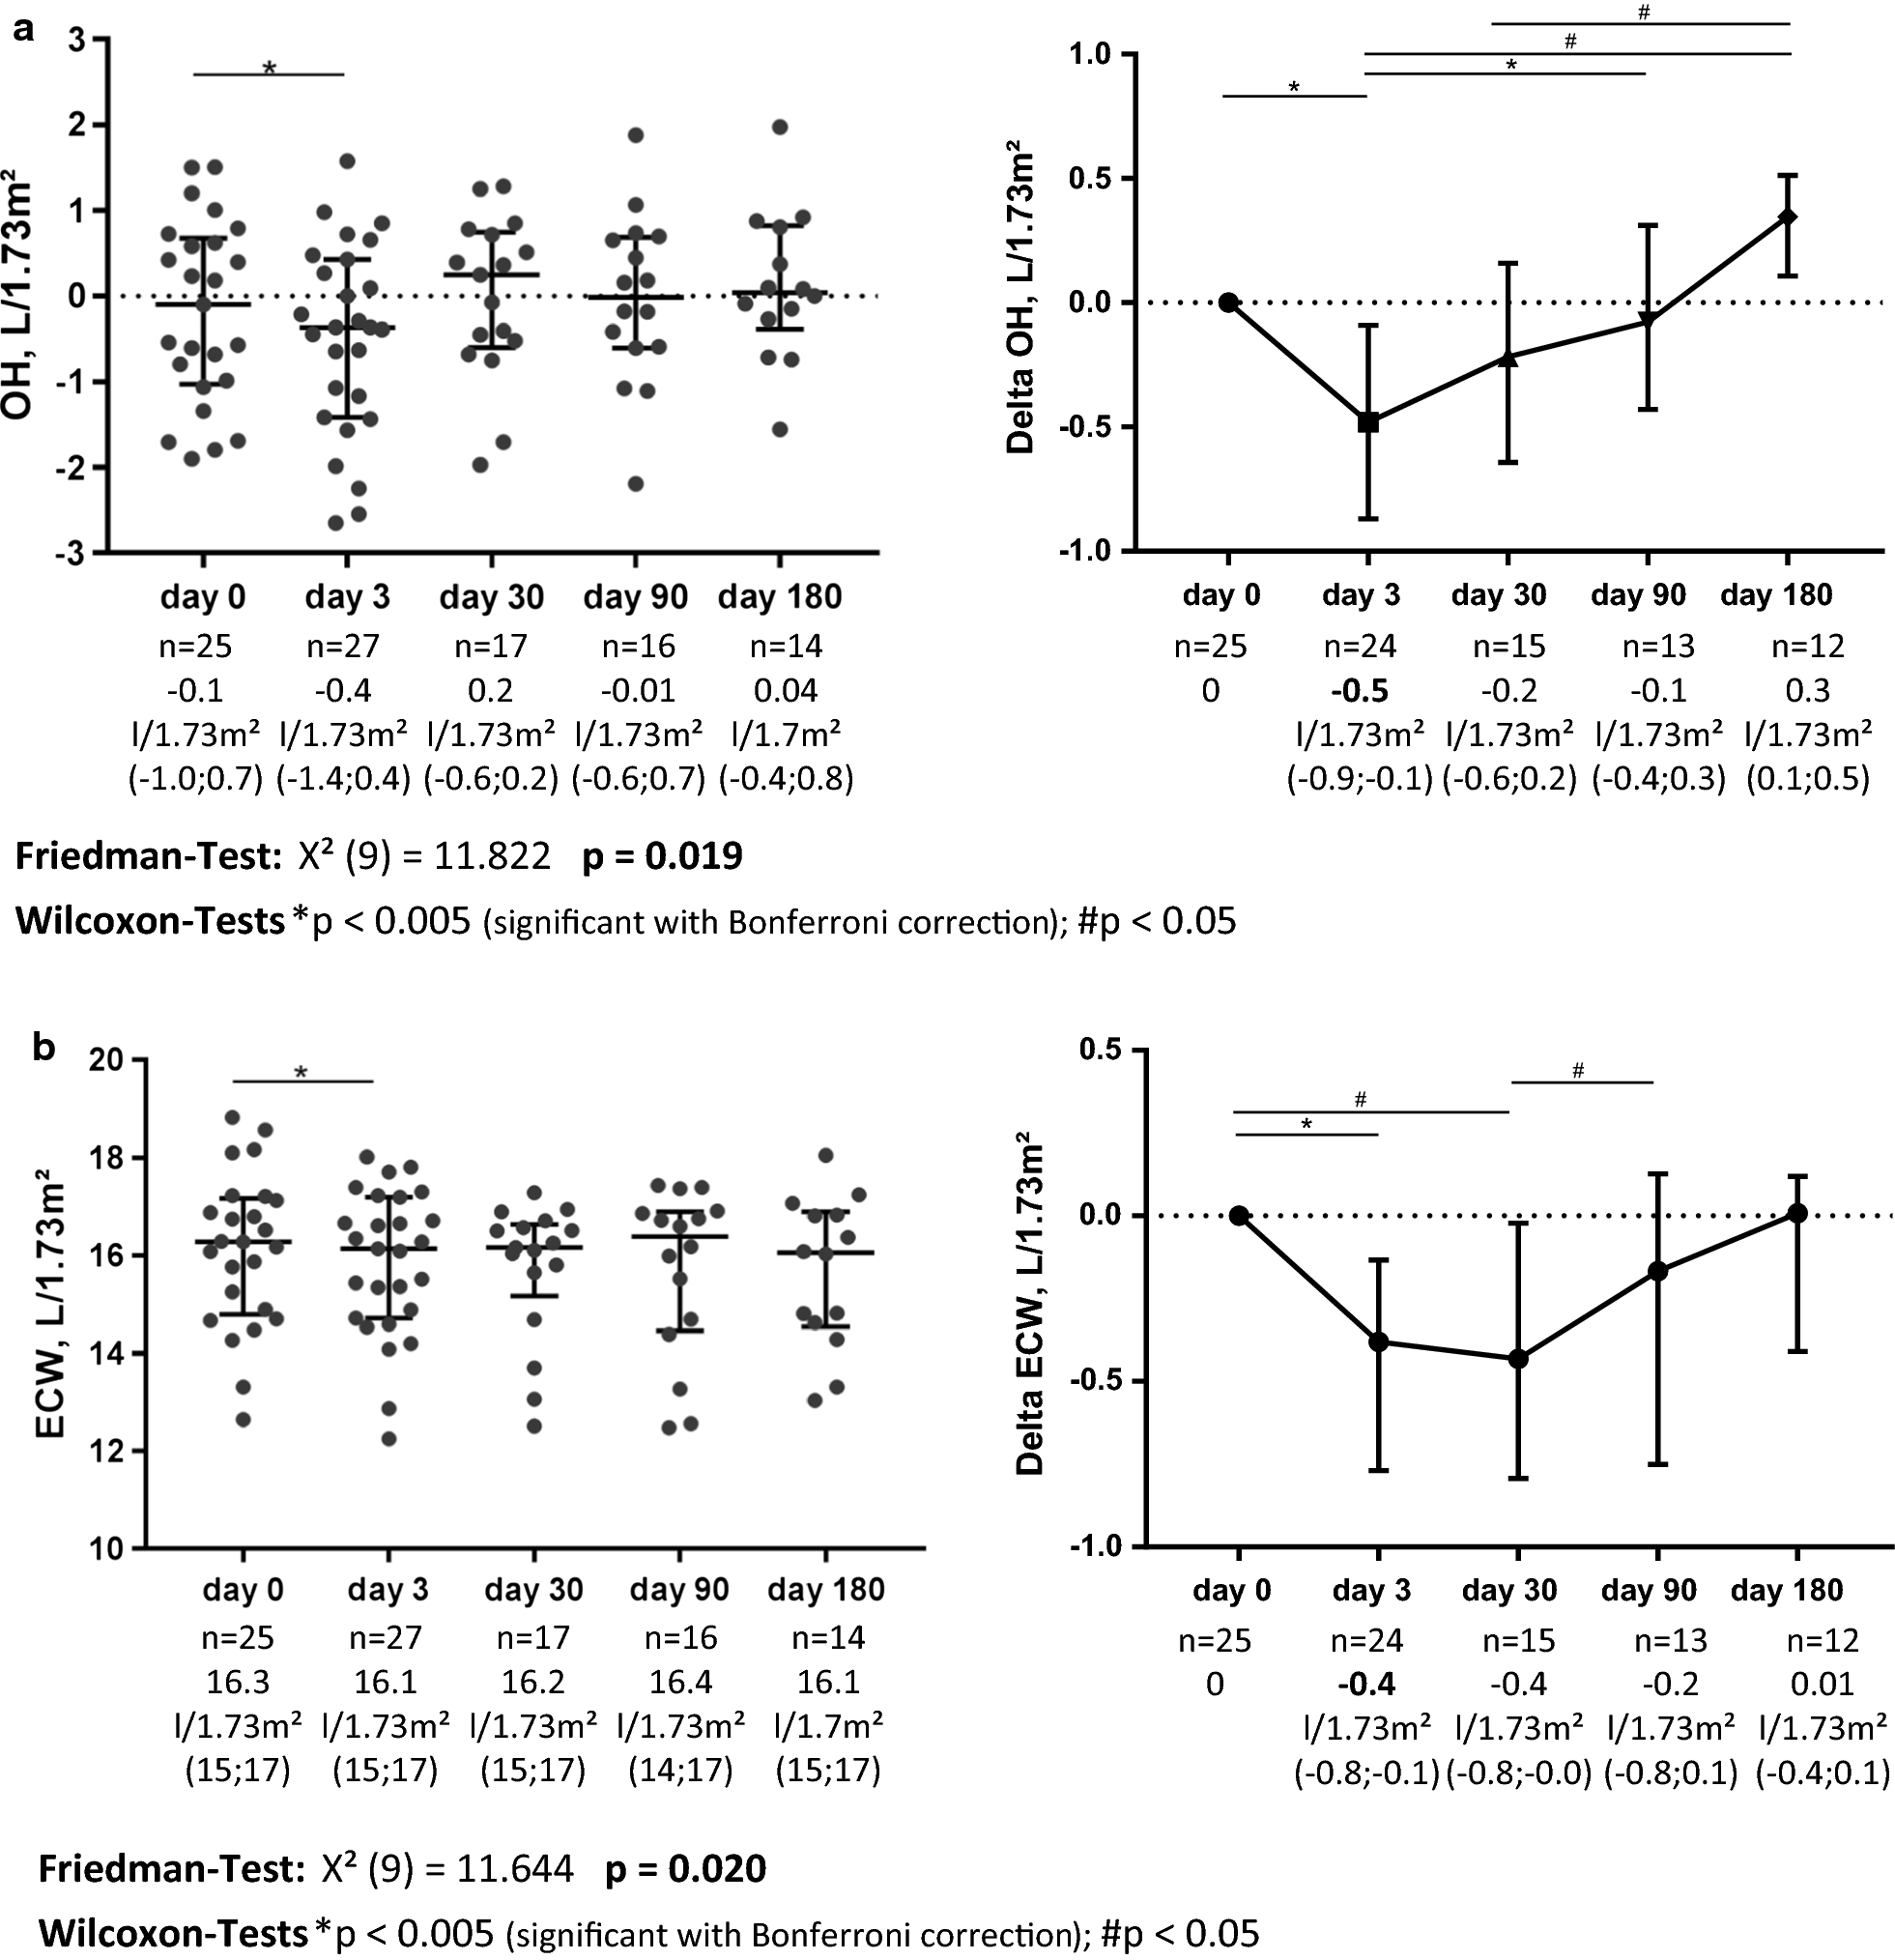
day 3にて、Overhydration (OH)  − 0.5 L/1.73 m2 (− 0.1; − 0.9)と細胞外水分 (ECW)  − 0.4 L/1.73 m2 (− 0.1; − 0.8)で、3−6ヶ月後初期値へ戻る


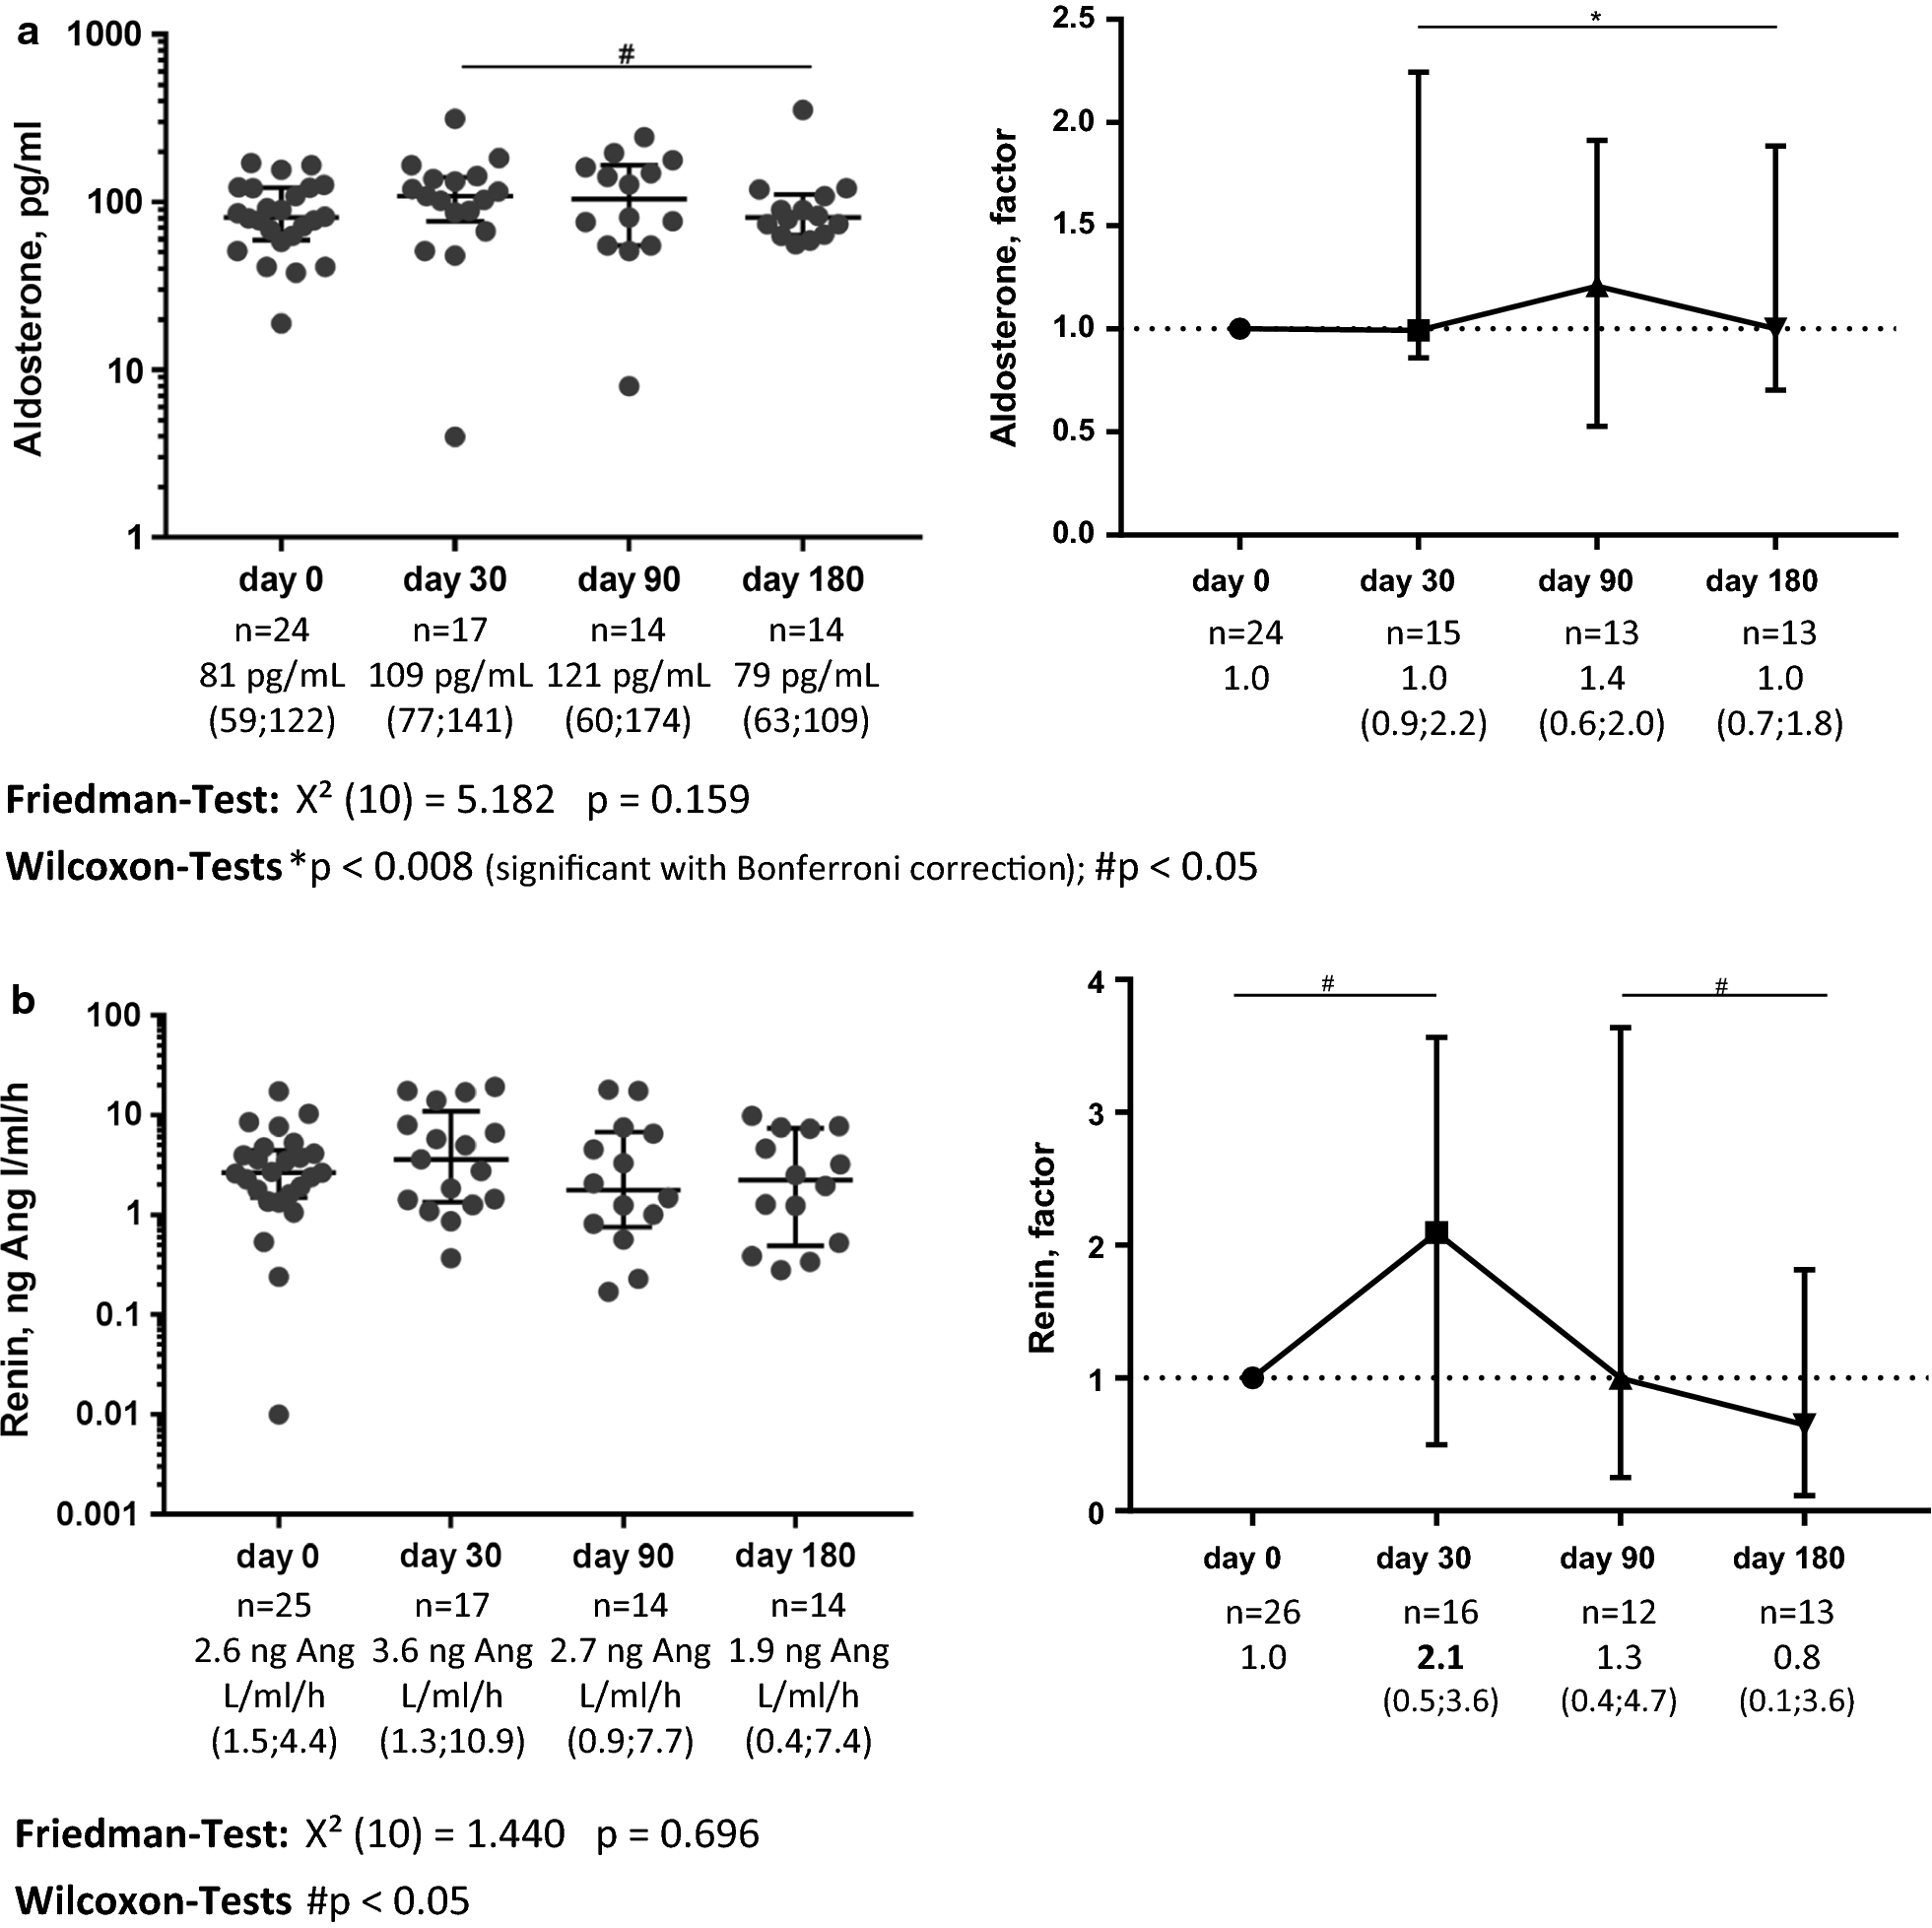
血中レニン活性 1ヶ月で 2.1倍(0.5; 3.6)増加、3-6ヶ月で初期値へ戻る

SGLT2i6ヶ月後の水分状況はヒドロクロロチアジド服用高血圧患者と健康者での差は認めず


empagliflozin 18名、dapagliflozin 9名の27名2型糖尿病外来患者

2型糖尿病患者へ長軸研究でSGLT2iの体組成、水分状況、RAASへの影響を検討
 bioimpedance spectroscopy (BCM, Fresenius)
http://www.fresenius.co.jp/pdf/BCM_catalog2015.pdf

体組成を第1週から6ヶ月後まで評価


食事サプリメント使用は米国成人の死亡減少へのベネフィットと関連せず

解説記事:
2019年04月11日 07時00分 サイエンス
サプリでは栄養素を適切に補えず過剰摂取時には死亡リスクを高めることもあるという研究結果
https://gigazine.net/news/20190411-more-vitamin-not-supplement/


Association Among Dietary Supplement Use, Nutrient Intake, and Mortality Among U.S. Adults: A Cohort Study
Ann. Int. Med. 2019
Fan Chen, et al.
DOI: 10.7326/M18-2478

【背景】食事サプリメントの健康ベネフィット・リスクは賛否あり
【目的】米国成人での食事サプリメント使用、食事及びサプリメントからの栄養摂取のレベル、死亡率の間の相関整評価
【デザイン】前向きコホート研究
【セッティング】 NHANES (National Health and Nutrition Examination Survey) data from 1999 to 2010, linked to National Death Index mortality data.
【被検者】米国成人(20歳以上)、食事サプリメント使用の質問への回答者 30 899 名
【測定項目】直近30日内の食事サプリメント使用と食事・サプリメントからの栄養摂取。アウトカムには総死亡率、心血管疾患(CVD)、がん死亡率
【結果】フォローアップ期間中央値 6.1年間、死亡 3613発生、CVD死 945、がん死 805
食事サプリメント使用既往程度では死亡率アウトカムと相関せず
ビタミンA、ビタミンK、マグネシウム、亜鉛、銅の適切使用量 (at or above the Estimated Average Requirement((栄養学)推定平均必要量関連語EAR) or the Adequate Intake level) は、総死亡率、CVD死亡率減少と相関するも、食事からの栄養摂取に限ったものであった。
カルシウム過剰摂取 (above vs. at or below the Tolerable Upper Intake Level(( 栄養学)許容上限量の高低評価)はがん死亡率増加 (多変量補正発生率比, 1.62 [95% CI, 1.07 to 2.45]、多変量補正発生率差, 1千人年あたり死亡 1.7 [CI, −0.1 to 3.5] )
この相関は、サプリメントからのカルシウム摂取関連と見なされる  (食事からの摂取と比較、≥1000 mg/d vs. no use: 多変量補正発生率比, 1.53 [CI, 1.04 to 2.25]; 多変量補正発生率差, 1千人年あたり死亡, 1.5 [CI, −0.1 to 3.1] )

Limitations:観察研究故残存寄与因子関与の可能性。食事サプリメントの報告はrecall biasに基づく可能性


【結論】食事サプリメント使用は米国成人の死亡減少へのベネフィットと関連せず


おそらく、マスコミ(テレビメディア)で、大々的に報道されることはないだろう


2019年4月10日水曜日

COPD予後指標 BARC


Predicting COPD 1-year mortality using prognostic predictors routinely measured in primary care
C. I. Bloom ,et al.
BMC Medicine201917:73
https://doi.org/10.1186/s12916-019-1310-0


54990名の被検者 UK電子カルテ使用プライマリケアCOPDコホート
初期コホート トレーニングとtest setへ均等ランダム化割り付け
外部データは2つめのコホート
12ヶ月死亡率推定リスクモデルCox回帰でbackwards elimination使用トレーニングセット
BMI、血液検査(B)、年齢(A)、呼吸変数(気道閉塞、急性増悪)(R)、併存症使用(C)を含む80の変数
具体的には・・・
FEV1, GOLD staging (FEV1 and FVC), C-reactive protein (CRP), albumin (low = < 35 g/L), haemoglobin, fibrinogen, platelets (low = < 150 × 109/L, high = > 400 × 109/L) and creatinine; creatinine above 120 μmol/L for males, or 110 μmol/L for females, was used to define chronic kidney disease (CKD). BMI was measured as kg/m2 (underweight < 19, normal = 19–25, overweight = 25–30, obese ≥ 30). Exacerbations, treated within primary (labelled as moderate) or secondary care (labelled as severe)

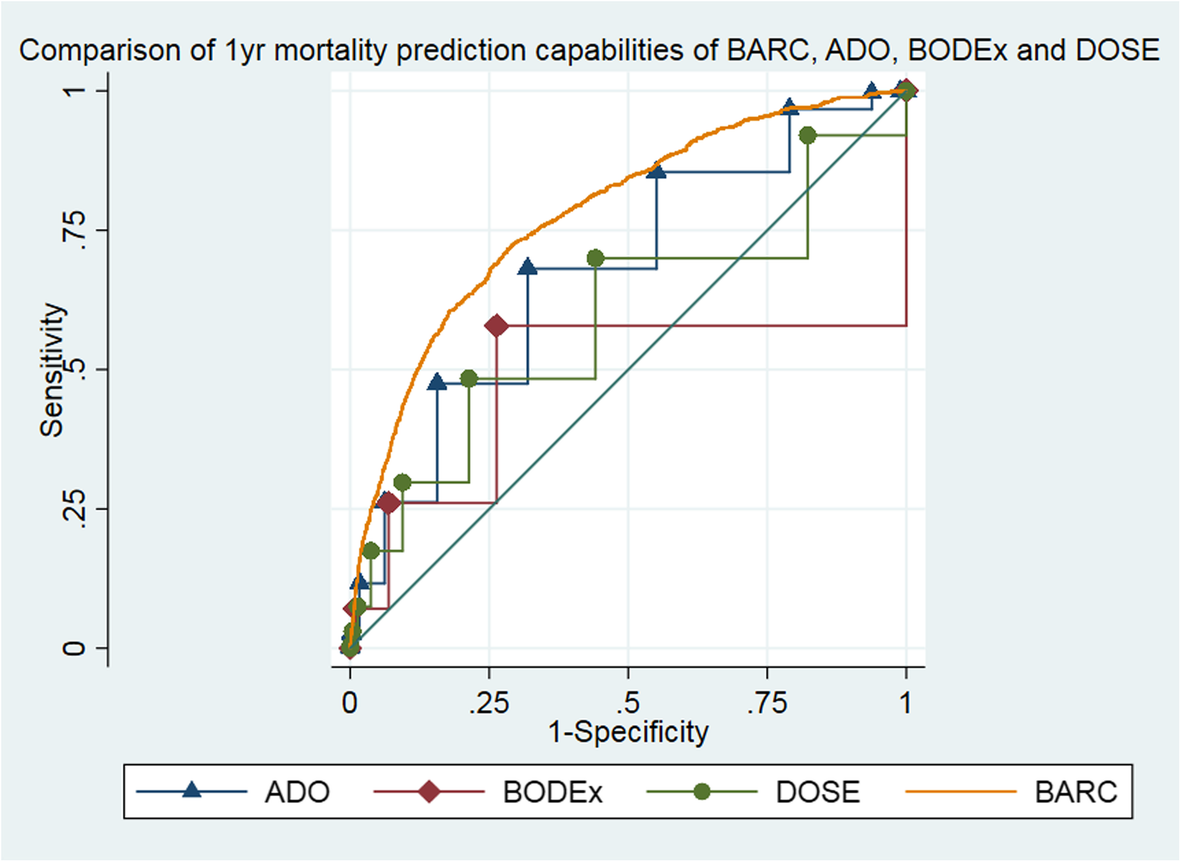
BODEx、DOSE、ADOと比較

リスクモデルでパフォーマンス推定

acceptable predictive performance
 (test set: C-index = 0.79, 95% CI 0.78–0.81, D-statistic = 1.87, 95% CI 1.77–1.96, calibration slope = 0.95, 95% CI 0.9–0.99; external dataset: C-index = 0.67, 95% CI 0.65–0.7, D-statistic = 0.98, 95% CI 0.8–1.2, calibration slope = 0.54, 95% CI 0.45–0.64)
acceptable accuracy predicting the probability of death
(probability of death in 1 year, n high-risk group, test set: expected = 0.31, observed = 0.30; external dataset: expected = 0.22, observed = 0.27)

BARCは既存の指数スコアよりspecialist respiratory variableなしでは優れている 
(area under the curve: BARC = 0.78, 95% CI 0.76–0.79; BODEx = 0.48, 95% CI 0.45–0.51; DOSE = 0.60, 95% CI 0.57–0.61; ADO = 0.68, 95% CI 0.66–0.69, external dataset: BARC = 0.70, 95% CI 0.67–0.72; BODEx = 0.41, 95% CI 0.38–0.45; DOSE = 0.52, 95% CI 0.49–0.55; ADO = 0.57, 95% CI 0.54–0.60)


転移性直腸結腸癌治療患者における高用量ビタミンDの効果

サプリメントにとってポジティブな話が一部あるが
・ビタミンD中毒の危険性配慮必要
・がん治療中の特殊な状況下での評価
これを忘れてはいけない

2つの報告を列挙
後者の報告で一部肯定的内容あり

ビタミンDサプリメントは消化器系がん患者において生存率を改善するか?
ランダム化臨床トライアル、417名の消化器系がん(食道〜直腸)患者において、5年再発なし生存率をビタミンD 2000 IU/日 vs プラシーボ比較し、 77% vs 69% 統計学的有意さ認めず
意義:ビタミンDサプリメントは消化器系がんの無再発生存率改善せず 
Effect of Vitamin D Supplementation on Relapse-Free Survival Among Patients With Digestive Tract Cancers: The AMATERASU Randomized Clinical Trial  Mitsuyoshi Urashima, MD; Hironori Ohdaira, MD; Taisuke Akutsu, MD; et al Earn CME creditEditorial: Insights From 2 New Trials on Vitamin D as Cancer Therapy; Elizabeth L. Barry, PhD; Michael N. Passarelli, PhD; John A. Baron, MD, MS, MSc

高用量ビタミンD3サプリメントは、進行・転移性直腸結腸癌患者における標準化学療法に追加したとき、無進行生存率延長するか?
第2相ランダム化トライアル、進行あるいは転移性直腸結腸癌患者139名にて、化学療法+大量ビタミンD3サプリメント vs 化学療法+標準量ビタミンD3にて、無進行生存期間 13ヶ月 vs 11ヶ月で、統計学的有意差なしだが、無進行生存・死亡に関する多変量ハザード比は0.64と統計学的に有意。
意義:進行・転移性直腸結腸癌患者における高用量ビタミンD3サプリメントにpotentialがあるかもしれない。大規模多施設RCT評価必要

Effect of High-Dose vs Standard-Dose Vitamin D3Supplementation on Progression-Free Survival Among Patients With Advanced or Metastatic Colorectal Cancer: The SUNSHINE Randomized Clinical Trial   
Editorial: Insights From 2 New Trials on Vitamin D as Cancer Therapy; Elizabeth L. Barry, PhD; Michael N. Passarelli, PhD; John A. Baron, MD, MS, MSc


a double-blind, multicenter, phase 2 randomized clinical trial called SUNSHINE was conducted to test whether vitamin D3 supplementation to raise plasma 25-hydroxyvitamin D levels can improve outcomes in patients with advanced or metastatic colorectal cancer. 
mFOLFOX6 療 法+ ベバシズマブ(Bevacizumab)は、血管内皮細胞増殖因子(VEGF)に対するモノクローナル抗体療法ベース

All patients received chemotherapy with a continuous infusion of 2400 mg/m2 of 5-fluorouracil (5-FU) over 46 to 48 hours, a bolus of 400 mg/m2 of 5-FU, 400 mg/m2 of leucovorin, and 85 mg/m2 of oxaliplatin (mFOLFOX6) plus 5 mg/kg of bevacizumab administered intravenously every 14 days per institutional standard of care (1 cycle = 14 days). Bevacizumab was allowed to be omitted during the first cycle and started with cycle 2 at the investigator’s discretion. 


Patients were randomized by a statistician (H.Z.) using computerized block randomization with a block size of 2 in a 1:1 ratio to concurrent high-dose vs standard-dose oral vitamin D3. The high-dose group received a loading dose of 8000 IU/d of vitamin D3 (two 4000 IU capsules) for cycle 1 followed by 4000 IU/d for subsequent cycles. 
The standard-dose group received 400 IU/d of vitamin D3 during all cycles (one 400 IU capsule plus 1 placebo capsule during cycle 1 to maintain blinding).
 Adherence to vitamin D3 was monitored using drug diaries and pill counts. Participants continued to receive treatment until disease progression, intolerable toxicity, or decision to discontinue treatment.


HPVワクチンをめぐる日本の"失われた8年"と、私たちが検証すべきこと

「子宮頸がんワクチン」という呼び方に、以前から違和感があります。 HPVワクチンが子宮頸がん予防に重要であることは間違いありません。日本では女子への定期接種として導入され、子宮頸がん予防を中心に説明されてきたため、この名称が広まった経緯も理解できます。 しかし、このワクチンが...